Thursday, 31 July 2008

And so it begins...


**Ring Ring **Ring Ring **Ring Ring **Ring Ring

- Hello, Occupational Health - Margaret speaking
- Good afternoon Margaret, my name is Michael, I’m one of the doctors due to start work at your hospital next week.
- Hello Michael, how can I help you?
- I received a letter from you asking me to call you. Something about missing information
- O.K., let me check my records can I have your full name and date of birth please?

I hear the tap-tap-tap of fingers on a computer keyboard and I try to visualise what Margaret looks like. In my head, I see a shortish woman in her late fifties with short, curly brown hair that is flecked with grey and a pair of large rimmed glasses that hang around her neck on a piece of string.

- Right, I’ve found you Dr Michael Anderson.
- That’s me
- Yes, I see what the problem is. We need some evidence that you are immune to T.B.

At one point I had a letter from an occupational health nurse confirming my TB immunity, but to be honest I have no idea where that letter is anymore. Probably among the many treeloads of paper that I’ve accumulated from “Induction Days” at previous hospitals

- I don’t think I’ve actually got any documents that say that
- I’m sorry doctor, but I can’t issue you with a “Fit to Practice” certificate unless I have some evidence that you are immune and you won’t be able to work without one.

My heart sinks a little at the thought of having to rifle through all the crap that’s currently in the “I Need To Sort All This Stuff Out At Some Point” box(es) under my bed. But then a thought hits me.

- I have a B.C.G. scar, I pipe up. - Is that evidence enough?
- Yes, that would be good enough, but obviously neither I nor any of my staff have seen your scar. Do you think you’d be able to pop in and show us?
- I live in NewCity! I can’t “pop in” because it’s about a two-hour round trip to your hospital. I do actually have an afternoon off this week but I don’t particularly want to spend it coming to show you my arm. Can’t I just come to the department to show you on Induction Day?
- Well, I suppose you could, depending on how many people we have to see that day, there may be a delay in issuing you with your certificate. You might have to wait a day or so.

I’ve already spoken to the anaesthetics office and it doesn’t look like I’ll be doing much actual clinical work in the first couple of days of the new job, so waiting a couple of days for occupational health clearance is unlikely to be a huge problem.

- O.K., well that’s fine with me. I’ll come in on induction day, and hopefully we can get it sorted then.
- Well, we shall see you then Dr Anderson
- Thank you. Bye for now
- Goodbye

**Click.

I hate Induction Day and it seems this time round, it’s starting even earlier than normal.

Wednesday, 30 July 2008

Another one leaves the flock


So, Dr Holly Branson has quit working as a junior doctor to work for her Dad instead.

I can’t say I blame her. In fact, I’m actually surprised that she’s remained in medicine for as long as she has. Why on earth would anyone want to work as a junior hospital doctor (for £21k p.a.) when their father is one of the richest men in the world? It seems that Holly has seen sense and has got out.

I wish her all the best (though I very much doubt she’ll need my good wishes).

Winding down...

After having a fantastic couple of weeks off, I’m back at work again. I think I’d gotten to the point where I needed a holiday. Getting out of bed had started to become even more of a chore than normal and I really wasn’t “throwing myself into it” as much as I normally did. Now I feel much more invigorated and am back to being super-keen again.

We junior doctors change jobs on the 6th of August. We move on to new positions, often in new hospitals and this is also the day that the brand new FY1 doctors start their first jobs. Lots of my fellow junior doctors appear to be on a “wind-down,” people are talking about where their next jobs are and what they’ll be doing there. Personally, I’m going to another District General Hospital and I hope to do quite a lot of work on the delivery suite.

Lots of the consultant anaesthetists and consultant surgeons are away on holiday at the moment, so there’s not as much work to do as normal and this adds to the “rest and relaxation” mood among the medical staff. It’s actually quite nice.

Some of the house officers are arranging a hospital ball on Friday, and I’m really looking forward to it. It’ll be a chance to get dressed up, a chance to share a drink or three with my colleagues, and also an opportunity to say goodbye.

Wednesday, 16 July 2008

Summer Holiday

Woohoo!

No more workin' for a week or two....

Thursday, 10 July 2008

Life-long learning 2


As I’ve said before, doctors should be committed to learning for the rest of our lives and the people we actually learn most from are the patients we look after.

Here are five things that I learned from my patients today:

1. Sea levels have been rising for the last 10000 years and are not rising any faster now than they were thousands of years ago, despite what the media say.

2. The needle didn’t hurt as much as she thought it would.

3. Christiano Ronaldo is a much better player than George Best ever was.

4. I look much younger than I am.

5. Just 2mg of midazolam can make a young man stop breathing completely.

Tuesday, 8 July 2008

Be careful what you wish for...

If you believe what’s said in the media, you’d probably conclude that our NHS is on its knees and on the verge of a meltdown. You’d think that primary care (GPs and A&E) is a complete disaster in this country and that it’s only a matter of time before the whole house of cards comes crashing down round our ears.

Despite this "obvious truth," it seems that people in other countries see what we have here in the UK as a good thing and are actually quite envious of our health service.

Funny that…

Free access to GP services is what I believe needs to happen. Then, and only then, will those on low incomes be able to take control of their health. Sure, it'll cost a hell of a lot of money. But if people could afford to go to their GP to get their cholesterol checked, to have their blood pressure measured, to talk about giving up the fags, then we could potentially claw back a significant amount of the money, while at the same time improving the nation's health.

But when you have the choice between paying 60 euro to have your BMI measured, or buy the tin of baby formula that your nipper needs, I know which most people would choose.


The full article is over here.

Friday, 4 July 2008

Am I a hypocrite?


I used to go running quite regularly, it was something that I really enjoyed doing. But, between studying and working and having a girlfriend, I hadn’t been for ages.


I went for a run last night and it was great. The sun was shining, but it wasn’t too hot and there was a slight breeze to cool me down as I ran. This country looks beautifully green at the moment and the people I passed seemed happy as they enjoyed the summer evening.

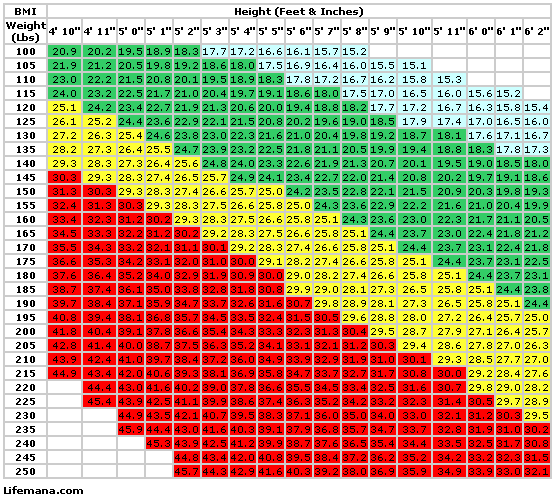
If I’m being honest with you though, I’d say that the real reason I went running was because I stepped on a set of scales the other day and discovered that I’m almost a stone and a half (9.5kg) heavier now than I was this time last year. On the BMI charts, I’ve slipped across the line from the Healthy Green to the Overweight Yellow. More tellingly, trousers that I bought because they were baggy are now looking distinctly “fitted.”

I’m not overly concerned though, nobody who knows me would describe me as “fat” and I’m sure the extra pounds will come off again, but it got me thinking about things I’ve said to patients about losing weight.

On many occasions, I’ve advised people that they need to lose some weight, that their size is damaging their health and on many occasions I’ve been exasperated when they “refuse” to do so.

“How hard can it be?” I’d whinge to my colleagues. “All they have to do is eat less and do a bit of exercise and then they would be in the hospital in the first place?”

But now, I’m officially overweight myself. So, do I have any right to tell another overweight person to lose some weight?

The question I’m asking is “Am I a hypocrite?”

And the honest answer has to be, “Yes, I am.”

I’m far from being alone in this though. In fact, I believe that the vast majority of doctors across the world have given advice to their patients that they, themselves flagrantly ignore.

I used to work with a consultant vascular surgeon who, every week for the majority of his working life would amputate people’s legs because their smoking had clogged their arteries, causing their leg(s) to rot. And every week, at the end of his list, he’d take himself off to the smoking room to have a few fags before reviewing the post-op patients.

Drunk people are so annoying in the A&E department. Not only because they can be loud, rude and aggressive, but because the effects of alcohol itself mimics the symptoms of severe disease (dizziness, drowsiness, slurred speech, vomiting etc…) and makes it much harder to exclude potentially serious problems. I used to bemoan having to clerk in drunk people on a Saturday Night but I knew that, had I not had to work, I would probably have been in the same bar, dancing like a tool and being almost as pissed as they are.

I know doctors that regularly take recreational drugs, even though they of all people know the harm these substances can cause.

What I’m saying is that there is a large amount of hypocrisy running through medicine and a large amount of the “Do as I say, not as I do” attitude that comes with it.

However, on the flip side of this, being a doctor certainly gives a different perspective of life and health. We’ve all seen people die in front of us in horrible, but avoidable ways and, as a result, we are morally and duty bound to try and help the person in front of us from doing the same.

I suppose what it comes down to is this. We are no angels, we never said that we were. I guess that our hypocrisy stems from wanting our patients to have as good a life as possible and from trying to get them to avoid the suffering that lies further down the path that they’re on.

We’ll continue to do this, even if we can’t take that advice ourselves.

Wednesday, 2 July 2008

Married to the job

Six Months ago...

I’m in the changing rooms, getting into my scrubs at the start of the day and I’m chatting with Jeremy, one of the other novice anaesthetists.

“I’ve started seeing someone,” I say

“Oh yeah?” Jeremy raises his eyebrow at me, “Who is she? Tell me more.”

“I’ve actually known her for a little while now, but things are just starting to get more serious. She’s fantastic though, and you know me, I don’t say that lightly.”

“What’s her name? Is she another medic?”

This is what you find in medicine. There’s the tacit implication that doctors only go out with other doctors and it’s almost as if you’re breaking the rules if you go out with someone totally non-medical.

“No, she’s not. She works in fashion, she’s called FashionGirl.”

“Oh that’s cool, so how did you meet?”

The conversation goes on along this vein for a few more minutes and then Jeremy leans into towards me and asks.

“Does she understand?”

“What do you mean?” I query.

“You’re planning to sit your primary exam this year aren’t you? Does she understand about the time you’ll need to study as well as spending so much time in this place?”

“Yeah, I’ve explained that to her.” I avoid his gaze as I say this because even in my own head, I’m not sure that FashionGirl really understands what lies in the few months ahead. I’m not going to be there a lot of the time. In the run up to my exams, I’m going to be married to my text books and there are going to be times when I’ll be so tired after work that I won’t want to speak to anybody at all.

“I’m sure it’ll be OK,” I continue, hoping that what I say will turn out to be true.

------------------------------------------------------

Last Friday Night...

FashionGirl and I are sitting having dinner and sharing a bottle of wine. I’d really been looking forward to seeing her because it felt like I hadn’t seen her in ages.

“You know, Michael” she says as she takes a sip and fixes me with her blue eyes, “I was really pissed off with you the other weekend.”

“When I said that I wasn’t going to come to Emma’s birthday do?”

“Yes. It’s not that you didn’t come, it’s that you said you would and then changed your mind the day before.”

“I know, but I’d just done a week of long shifts and I just wanted a night in.”

“I know that babe, but…” her voice tails off.

“But?”

“I don’t think it’s very fair that’s all. It’s just that sometimes it seems like I’m the one making all the effort. I’m always the one that comes over to see you. I know that you’ve had your exams and everything, but I feel that I’ve been really supportive over that whole period.”

“You have!” I interject as I recall her sitting in bed with me, quizzing me about the Gas Laws. “Very much so.”

“But, it seems to me that now you’ve got this free time that you could be making an effort too.”

“FashionGirl,” I say. “Remember that was my first free Saturday in weeks and I’ve been over to see you loads in the last couple of weeks.”

“I suppose that’s true.”

“And besides, I don’t think I would have been a whole lot of fun that night and, had I gone out with you guys, I reckon I would have spent most of the evening asking you to come home with me. I was in bed by 8 that night!”

“Actually, I’ve been meaning to have this chat with you for a little while now.” I continue. “There will be times where I won’t be able to do things that I said I would. There will be times when I miss doing something with you because of my job and there’ll be time where I really just want to be left alone and just sit in a dark room for a while. But please remember that all of that is just because of the job I do. It doesn’t mean that I care about you less, because I care about you loads, you know that.

“I remember in my first year after graduating, after a real nightmare shift, I called up my Mum and Dad and ranted and raved about how I was spending all my time at the hospital and it seemed I never got to do anything else.

“They said to me, ‘Son, it’ll only be for the first couple of years you know. As you move up the ladder, you’ll have to do less work and you’ll have more free time in a couple of years’ time.’

“But that’s not true, FashionGirl. It’s really not true at all. The higher I get up the medical career ladder, the greater my responsibilities get and I’ll be doing more work and have more commitments - not less. And that means that going into the future, this problem is just going to get worse.

“What I mean to say is that I do really care about you, you know I do, but there will be times when I let you down. All I can say to you is, when the choice is in my hands, I promise I’ll put you first. It’s the best I can do.”

Tuesday, 1 July 2008

The Crash Team

When somebody dies on a hospital ward, a “crash call” gets put out by a member of the ward staff. This comes through to the pagers of the members of the “crash team” who have only a couple of minutes or so to get to the ward and attempt to literally bring the dead person back to life again.

There is a definite order in which the various members of the crash team arrive at a cardiac arrest.

First there are the nurses due to the fact that they are actually on the ward when the person died and are often the people who put the crash call out in the first place. There’s usually two or three nurses there performing Basic Life Support (CPR) before the crash team arrives.

The first member of the crash team to get there is the Medical SHO. The Medical SHO is usually younger, quicker and keener than the other members and will try her best to organise a working airway, IV access, a heart monitor and give some emergency drugs.

The Medical SHO is quickly followed by the Medical FY1, who is even younger and fitter that the SHO, and would have been there first apart from the fact that he doesn’t want to get there, get scared by the situation and freeze with everyone looking at him and asking “What shall we do now, doctor?”

It takes about a minute or so for Advanced Life Support to get properly underway, and this is the moment when the Medical Registrar pitches up. The Medical Registrar is the leader of the crash team and she’ll have seen literally hundreds of these in her time. She’s got the knack of arriving early enough to potentially make a difference to the patient but late enough to allow the initial panic to die down and for everyone to slot into their roles so she can take over the overall running of the crash call.

Last to turn up is the anaesthetist. It seems that the anaesthetist’s role at a cardiac arrest is to turn up, sneer, suggest to the Medical Registrar that we should all stop now and then saunter off again. I used to think that this was because anaesthetists were lazy, but now I know that the reason we turn up last is because most of the time, cardiac arrests happen on general medical wards and in most hospitals, the general medical wards are nowhere near the operating theatres, which is where the anaesthetists hang out. The other reason is that the medics are perfectly capable of running the arrest without us, so we don’t bother making the long sprint from theatres to the medical ward (up to half a mile in some hospitals) and settle for a slow jog instead.

Saturday, 28 June 2008

It's Saturday


Thursday, 26 June 2008

So long, farewell, auf wiedersehen, adieu


It's with great regret that I bid farewell to two of my favourite bloggers.

Surly Girl and Mousie, I'm going to miss you.

All the best,

- Michael


Wednesday, 25 June 2008

Making a difference


I had such an amazing day at work today. In my time working at NewTown Hospital, I hadn’t really done any maternity work so, I was pretty excited when I found my name on the maternity rota for today.

I pitch up at the delivery suite and have a chat with the overnight anaesthetic registrar, who filled me in on how the suite worked and what sort of things I would be expected to do. It all seemed pretty straight forward. A few minutes later on, the consultant of the day, Dr Shah, pitches up and we go and investigate what work we were going to have to do.

There were two ladies who needed elective caesarean sections (C-Sections) and the Obstetric consultant told us that there were a few ladies on the unit that would probably need emergency C-Sections as well.

As a rule, women like to be awake when they have their C-Section, so they can see their baby straight away. This means that we give them a spinal anaesthetic (basically an injection into their spine to numb the nerves there so they can’t feel anything from their chest down).

I’ll be the first to admit that I’m not really very slick with my spinals. The technique is “blind” which means that you can’t see where the needle is going. So, what you have to do is imagine the 3-Dimensional anatomy and relate that image in your head to where you think the tip of your needle is and where you think it needs to be. I’m getting better at them though, and was glad of the opportunity to do a couple more today.

The first lady was called Mandy and she was almost exactly the same age as me. Mandy was very relaxed about the whole thing and said she understood what was about to happen – obviously the prenatal counsellors had done a good job. Her partner, James, on the other hand, was obviously a huge bag of nerves.

Dr Shah did the spinal anaesthetic and, in the process, talked me through how she likes them to be done. Once we were happy that the anaesthetic was working, we gave the surgeons the nod, and they cracked on with doing the caesarean section. 15 minutes later, they had the baby out and the room echoed to the sound of a baby crying as Mandy and James’ baby boy took his first breath.

Welcome to the world, little one.

Dr Shah let me take care of the next lady pretty much all by myself. Mrs McAllum was due to give birth to her 4th child. We’d already seen her in her room to let her know what to expect, to give her information about the procedure and allow her the opportunity to ask any questions or raise any concerns that she had.

The nurse went off to fetch Mrs McAllum and I checked all the anaesthetic equipment in theatre, I drew up the inotropic drugs that I would need and checked that my emergency drugs were drawn up and were readily available.

After siting a cannula into her hand and attaching her to a bag of fluids, I went to scrub up. I got all my equipment ready and made sure Mrs McAllum was in a good position and then I started.

First some local anaesthetic into her back and then I tried to find her subarachnoid space with the spinal needle. I couldn’t. I didn’t feel like I was hitting any bone, so I kept advancing the needle until it was all the way to the hilt, but still I wasn’t in the right place. Spinal needles are 12cm (approx 5”) long and Mrs McAllum wasn’t a particularly fat, so I thought I must have missed. I tried again but with the same result. Eventually, Dr Shah got bored of me poking around in this woman’s back and she got scrubbed up and took over. It turns out that, amazingly, the standard needle was too short for Mrs McAllum, and once we changed to an even longer needle, we were able to find the correct place and give her the injection.

The consultant obstetrician struggled for a while with the operation, but got there in the end and soon enough, Mrs McAllum’s fourth child, a boy, was breathing quietly in his Daddy’s arms.

Welcome to the world, little one.

In the afternoon, we helped two more women give birth. Their babies both had “foetal distress” and they needed emergency caesareans to prevent the baby from possibly being brain damaged or even dying. For the first lady, we had enough time to get a spinal in and working, but we had to give a general anaesthetic to the second lady.

All in all, it was a fantastic day. I was able to help these women during childbirth and, in the process, felt I made a real difference. I saw four babies being born and there were four very happy couples. The birth suite seems to be a very happy and enjoyable place to work and I was grinning from ear to ear as I walked out of the hospital at the end of the day.

I love my job.

Monday, 23 June 2008

The European Working Time Directive


In just over a year, the European Working Time Directive (EWTD) comes into full force for junior doctors. The directive will state that it will be illegal for our employers to make us work more than 48 hours each week. As things stand today, we are meant to be working a maximum of 56 hours – at least, in theory.

The general consensus among the junior and senior doctors that I speak to is that the EWTD is a bad thing. It’s a bad thing because it reduces the amount of experience that doctors in training have, it reduces how often we are exposed to and have to deal with a given situation. In the long run, it will lead to consultants being less qualified and less capable than they used to be, and thins will have a damaging effect on patient care.

The other, more pressing reason why the EWTD is a bad thing is because there will be a lack of continuity of care for the patients. In the old days, a patient coming into hospital would be seen by two or three doctors during their hospital stay. The EWTD means that the same patient could be seen by six, seven or more doctors. The said doctors won’t necessarily know all the details about the patient or what their colleagues have said or done, so as a result, things get duplicated or omitted and patient care suffers.

There has been plenty written about the problems implementing the EWTD and there have been calls from many individuals and organisations (including the excellent Remedy UK) for doctors to be made exempt from the EWTD, that is, that we should be working more than 48 hours a week.

I disagree with this.

I take the minority view that the EWTD is actually a good thing and will improve things for doctors and, more importantly, for our patients. Let me try and explain.

First of all, let’s not lose sight of what we are talking about here. At the moment, we are meant to work no more than 56 hours per week, the EWTD makes it illegal for junior doctors to work more than 48 hours every week. Given that the standard working pattern in this country is 9am to 5pm, then we are talking about a reduction from working 7 days a week to working 6 days a week.

Working 6 days a week is plenty of time. Working 6 days a week for nine years (for hospital specialties) is a long enough apprenticeship. (Remember, that all this comes after spending five years at medical school). After working 6 days a week for nine years, I think that doctors would be confident that they could deal with just about anything that their specialty could throw at them.

Working 6 days a week is plenty, PROVIDED THAT YOU ARE BEING TRAINED.

This is the real problem that medical training faces, if you ask me. As a junior doctor working in General Medicine or General Surgery, I spent so little of my time learning useful stuff, it was untrue. The vast majority of my time was taken up with form-filling, chasing results, phlebotomy, re-writing drug charts, cannulation and arranging discharges from hospital. As a proportion of the average working day, the time I spent learning about and trying to understand the management of the patients I was looking after was small. The time I actually spent managing the patients myself and taking decisions was minimal. The consultants were pretty unhelpful (sometimes spectacularly so) when I tried to find ways of improving my training.

The sad fact is that most of the time I was at work, I was learning little that was new. Cutting back on this time won’t make me a worse doctor, provided I still get experience of the important parts of clinical decision making and management.

The surgeons are talking about the cuts in their operating times and the consequent reduction in their experience. This may be true, but this has little to do with the EWTD and much more to do with NHS hospitals trying to save money.

It goes like this. The hospital gets paid by the Primary Care Trust (PCT) for each operation done at the hospital. A senior consultant can do an operation much faster than a junior registrar or SHO. So, in order to make more money, the hospital gets the senior consultants to do the vast majority of the operations. Good for the hospital, good for the patients, bad for the training of junior doctors.

I very rarely see the junior surgical doctors in theatres, but I remember as a medical student, the SHOs and SpRs had their own theatre lists of simple operations. This doesn’t happen anymore and I think the real reason why our surgeons aren’t getting the training they want is nothing to do with the EWTD and everything to do with the bottom line.

The message is simple: we juniors want to have proper training when we are at work. We want to be interpreting CT scans and making decisions based on them (under appropriate supervision, of course), we want to be diagnosing and treating medical emergencies, we don’t want to be filling endless reams of discharge forms and other paperwork.

The continuity of care issue is a tougher nut to crack, in my opinion. It is much better if all the doctors, nurses and paramedical staff know everything about each patient and understand what the plans for that individual are. However, this ideal is very difficult to achieve with the shift system that the EWTD necessitates. I don’t think that going back to the old “the same doctor will be here all the time” system is the way forward.

Let’s not forget the downsides to working very, very long hours.

I’m young enough to have avoided the days when junior doctors started work on Friday morning and didn’t leave until Monday evening, but I’m old enough to have done runs of 15hr and 24hr shifts and let me tell you, they are far from fun.

You can do one or two long shifts and still function quite well, but after five, six or seven on consecutive days, it can become a nightmare. You rarely get chance to eat properly on these shifts and you become ridiculously tired because you’ve hardly had any sleep. What happens is that you become really emotional, really bad-tempered and after a while you get to a point where your brain becomes like mashed potato. You can’t think straight and you find it difficult to summon the energy to even move.
But your pager doesn’t stop going. The patients don’t stop coming in and they all have to be seen and treated because they all need your help. So, I ask you, when you get called to see little Mrs Robertson, the 83 year old lady from a nursing home with multiple medical problems who’s come in because she’s “not eating much” and all your body wants to do is eat something and lie down for a bit; are you really going to pick up the super-added pneumonia that she has on top of her worsening heart failure? Are you? Really?

The worst thing about working really long hours is that you become really resentful. You become resentful of the hospital, resentful of your decision to become a doctor and, worse of all you become resentful towards the patients. You start to feel animosity towards the very people you’re supposed to be helping and that is a really horrible thought situation to be in. You feel awful about yourself for thinking those thoughts, but you can’t stop yourself because, ultimately, what is standing between you and the sleep that you crave are the ill patients you have to look after.

There are huge rafts of evidence that point to the fact that tired doctors make bad decisions and the care of patients suffers. I think the opponents of the EWTD should be very careful what they wish for. Like I say, working six days a week is enough.

I love my job as a junior anaesthetist. Since I left General Medicine, it’s been a breath of fresh air and I’m really enthusiastic and passionate about what I do and about caring for my patients. I think a huge part of the reason for this is the way that anaesthetic training is set up.

In the last ten months, I’ve given over 300 anaesthetics to patients. In that time I have had outstanding support from my seniors, but have been given enough space to get on and do things by myself. The paperwork I have to do is minimal and is to-the-point and useful and most importantly, people leave me alone to get on with my job. There’s no expectation that I should be in four places at the same time.

I’m working a 48-hr EWTD compliant(ish) rota and it means that I don’t go home feeling shattered and pissed-off with my job. I have the time and the inclination to do things outside the workplace and my life is much happier for it. I found myself looking up the route of the median nerve in my anatomy book after work last week, I would never have done that if I had to work more hours. I think all-in-all the training I’m getting in anaesthesia and the free-time that the EWTD allows is making me a better doctor, not a worse one.

I think the other medical specialties should look at the way training in anaesthesia is structured and take a leaf out of that book.

Working 6 days a week is enough.

Wednesday, 18 June 2008

Money, money, money


There’s loads in the news about the economy today and how the credit crunch and rising commodity prices mean that we’re all going to have less money for the foreseeable future. I’m quite annoyed by the fact that there are economists all over the telly telling everyone how “it would be really dangerous if public sector workers got pay rises.”

We junior docs got a 2.2% pay increase this year, despite the fact that inflation is at 3.3% and set to rise. I think it’s ridiculous to say that the city workers and bankers who caused the credit crunch can take home six-figure salaries and five-figure bonuses, but that doctors and nurses are not allowed a pay deal that keeps up with inflation.

The thing is being a junior doctor is an expensive business. I was working out exactly how expensive during a theatre session this afternoon and I came up with this list of fees that I have to pay this year in addition to the usual travel and clothing costs that every worker has to pay.

FRCA Primary MCQ Exam Fee: £260
General Medical Council Registration Fee: £390
Medical Indemnity Insurance: £60
Membership of the AAGBI: £55
FRCA Primary OSCE/Viva Exam Fee: £450
Anaesthetic Textbooks (to date): £175
Advances Trauma and Life Support Course Fee: £550

Total: £1940!

Looks like I won’t be going on holiday this year…

Monday, 16 June 2008

Things have come a long way


One of the patients on my list today was a young chap who had come in for a repair of his hernia. It was all pretty routine stuff, but what struck me about this guy is that he was seriously BUILT in that he was about 6’4” has huge muscles all over. I chatted to him for a bit in the anaesthetic room and it turns out that this guy is a boxer and was very disappointed to have to have surgery as he was hoping to turn pro at the end of the year.

I had a few reservations just because of his sheer bulk, but he actually turned out to be really easy to anaesthetise. He had huge veins and the fact that he doesn’t smoke or drink meant that I had very few problems with him on the table.

Once he was “under” I turned to the theatre nurse, Adam, and said, “Tell you what, I certainly wouldn’t fancy my chances in a fight against this guy, look at the size of him!”

To which Adam replied, “yeah, but remember that you’ve got the drugs, so you’ll always win!”

The drugs we use these days are pretty damn good in my opinion, but as Knowmore writes, this wasn’t always the case…


The kindly patient's left hand threw the Surgeon to the ground and his
right-hand the scrub nurse into the sink. He then determined to leave the
operating theatre by the simple process of running up the staircase with me
still attached round his neck, the mask clamped determindley to his face

Friday, 13 June 2008

Results Day


The Royal College of Anaesthetists (RCoA) said that they’d publish the exam results yesterday. I figured that it was unlikely that the results would be out first thing in the morning, so I waited until the end of the morning theatre list before looking. I nervously logged on to the computer and went on to their website only to be greeted with a message saying something like “we are still checking and verifying the results and we hope to publish them before 5 o’clock today.”

Great.

I continue doing my job and at 16:30, I wander round to the computer terminal in the operating theatre and log on again. It’s there. There’s a link that says Primary MCQ Pass List.

At this point, I’m physically shaking. My mind briefly flicks back to the weeks and weeks of work I put into sitting this exam. To the stag parties, house parties and sports matches I’ve missed because of my study schedule. I think once again of how fucking depressed I’ll be if all that has gone to waste. I’ve been speaking to the SHOs and registrars in the last week or so and none of them who have passed this exam answered anywhere near all the questions on the paper (negative marking) and I thought that perhaps my gung-ho attitude to the paper was a little foolish.

Anyway, all that’s behind me know and and shake my head, take a big breath and click the link.

A .pdf file opens and the hospital computer system slowly downloads its contents. I look around at my patient on the table, she’s fine, completely stable and well anaesthetised. I look back and the file had opened.

It’s a simple list of numbers with the word “PASS” in blue next to each number. I realise that it’s a list of our candidate and royal college numbers and there were several missing from the sequence e.g. numbers 100 and 102 were on the list but 101 was not. Basically if your number was on the list, then you had passed.

I quickly scroll down a couple of pages to where my number should be.

I look.

I look again.

I check my candidate number on the letter that the RCoA had sent me.

I look again.

It’s there!

I check the letter again.

I look again.

It’s definitely there!
Without a shadow of a doubt.

I’ve passed!!

“Come on!!” I shout. “That’s what I’m talking about!” This causes everyone in the room to stop and look round at me and I beam back at everyone.

“I just found out I passed my Anaesthetic Primary MCQ Exam.” I state and I get lots of “Well dones” and “Congratulations” in response.

This means that all the hard work I’ve put in was time spent well and, more importantly, I effectively get most of the summer free of study so I can really enjoy myself. And enjoy myself, I will.

I spent the rest of the day feeling generally pleased with myself and letting every single person I bumped into, doctors, nurses, patients and porters know what I’d achieved.

I was laughing all the way to the bar.

Wednesday, 11 June 2008

Hospital Trekking

One of the parts of my job as a junior doctor that doesn’t often get acknowledged is its physical aspect.
I was on call today and as part of my duties I visited main theatres, three surgical wards, the intensive care unit, the discharge lounge, two medical wards, day case theatres, the surgical assessment unit, the paediatric ward, the Department of Anaesthesia offices, the gynaecology ward and A&E resus.
Trust me, it’s a LOT of walking (and sometimes running) and after a 13hr shift, I frequently come home with my legs aching and my feet throbbing, just like they are now, in fact. I’d actually be interested in how far I walk on a typical on call shift, maybe I should get one of those pedometer thingies and find out.

Monday, 9 June 2008

The Exam


I’ve not written much over the last week or so because I’ve mainly been down the pub after sitting my first post-graduate anaesthetic exam last Wednesday. Now the hangovers have gone, I thought I’d write a little about how I feel about the whole process. I’ll warn you now that this post is probably not going to mean a fat lot to the non-medical readers, but it’s something that has taken a hell of a lot of my mental energy recently

On sitting it early.

Traditionally, the Royal College of Anaesthetists (RCoA), who set the exam, wouldn’t let doctors even attempt the paper until they had done a minimum of 18 months work as an anaesthetist in a recognised training job. The MMC shake up to post-graduate training has meant that they’ve relaxed the rules about this and now say that you can sit the exam once you have your “Certificate of Basic Anaesthetic Competencies” which takes about 3 months to get. They haven’t changed the examination itself, so by deciding to sit the exam early (after 10 months as opposed to 18) I was putting myself at a potential disadvantage.
Advice from the consultants and registrars who have passed the exam varied. Some strongly advised me to wait for another few months and sit it in September (13 months in), whilst some said that I may as well get on with it so it’s out of the way.
I decided to go for the early option because the exam is theory based, so passing it is more a matter of doing loads of book rather than practical experience. Also, should I fail, I can get another crack at it in September and still be on course so pass all parts of the exam by the end of 2008.
Whilst studying, it became apparent that experience IS important. For example, there’s lots of stuff about pregnancy, its physiological changes and about how regional and general anaesthesia is different in a pregnant woman. Now, I’ve done absolutely no obstetric anaesthesia, so I had to learn all the facts “dry” as I had no real experience to relate them to.

The run up

I worked really hard to study for this exam. I mean really hard. I was putting in 3 hours of study after a working day and up to ten hours on the weekends. The spectre of being stuck in New City for a whole year longer was more than enough motivation to keep me in my revision chair. In the last week before the exam I think I was starting to go a bit stir-crazy. I was having headaches all the time and found it really tough to concentrate. I think probably pushed myself a little too hard, but this exam is notorious for being the hardest post-grad exam of all the specialties so it was a case of “needs must.”

Negative Marking

The exam paper itself is a multiple choice paper that asks 450 True/False/Don’t Know questions. The paper is negatively marked, so you score 1 for a correct answer, 0 for a “don’t know” and -1 for an incorrect answer. The pass mark is about 55%.
This is the last time that the RCoA are using negative marking and good riddance is what I think. A pass mark of 55% on a negatively marked paper means that if you decide to answer all the questions, then you need to get just over 75% of what you’ve answered correct. If you decide to pass on some questions, the percentage of correct answers you need to give goes up too. So there’s a balance between answering enough questions to pass the paper and not guessing at questions and picking up negative marks.
Lots has been said about various approaches to negatively marked papers and how many questions is the “ideal” number to answer. To be honest, it was all too complicated for me, so I decided to keep it as simple as possible and answered just about every single question on the paper. This is a high-risk strategy because it means I’m more likely to fail if I haven’t done quite enough work, but it also means that I’m more likely to score very highly if I have - “Live by the sword, die by the sword.”
I based my study and revision timetable round doing as many practice MCQs as I possibly could. I borrowed books like QBase and the RCoA Blue Books and I went on websites like onexamination.com and frca.co.uk. In my opinion, some of these resources aren’t as helpful as they claim to be and were a bit of a waste of money. I was particularly disappointed with Onexamination.com in particular as it is out of date, and gives far too much weighting towards the random minutiae rather than the core knowledge that you need to pass.

Pre-exam chatter

I really don’t like chatting to other candidates before exams and before interviews. The conversations you have are utterly pointless and talking to other people only makes me feel worse about my prospects for passing. I arrived as close to the exam start time as I dared to and took myself away from everyone else to sit on the floor in the corner. It’s not that I’m anti-social, it’s just that I think there’s a time and a place for chit-chat and the lobby to the exam hall isn’t it.

The exam itself

I think the exam itself was tough, but then again, I was expecting it to be very tough. What I’d say about it is that I thought the exam was fair. The vast majority of the questions were based around core anaesthetic knowledge and the drugs that you’d reasonably expect an anaesthetist to know about. There was very little in the way of random, irrelevant trivia, so I can’t really complain about the exam questions themselves. As always with these things, there were bits that I knew right of the bat, bits I had no idea about and those annoying questions where you can remember reading the information but just can’t recall the actual answer. I was thanking my lucky stars that I flicked through the section about skeletal muscle in my histology book but was kicking myself that I neglected to learn how ketamine is metabolised.

Post-exam wind down

It feels fantastic to not have to study anymore. I can come home and just do normal things like watch TV, go for a run and cook dinner without the constant incantation of “I should be studying, I should be studying, I should be studying” going round and round my brain.
I honestly have no idea whether I’ve passed or failed, but I really do think that I’ve probably worked as hard as I possibly could have done. Fortunately, the RCoA don’t hang around too long with the marking and I will get my results on Thursday.

In the meantime, my life has quickly reassumed a familiar pattern – and it’s back to work again tomorrow.

Monday, 2 June 2008

Thank you

A big thank you to all who wished me luck for my exam tomorrow. It feels like I've been eating, sleeping and breathing anaesthetic facts and trivia for the past six weeks and I am sooooo looking forward to it being all over in less than 24 hours!

This time tomorrow, I'll be in the pub.

I can't wait.

Thursday, 29 May 2008

I’m feeling focused

At the start of the year, I made a promise to myself. I promised that I would spare myself the trauma of applying for jobs this year, and I would focus on passing the Fellow of the Royal College of Anaesthetists (FRCA) Primary Examination instead.

That was the talk, now it’s time for action. The first (MCQ) exam is next Tuesday, meaning I have only a few days left of study to go. I’ve not been blogging much recently because I’ve been working really hard over this past month or so – sometimes putting in nine or ten hours study per day. To be honest with you, this exam is rock hard and very soon, I’ll find out if I’ve done enough work.

Though my study period so far, I’ve been through self-delusion, pontification and despair, but in the last fortnight I’ve developed a sort of gritty focus that will hopefully see me through.

The exam is negatively marked and the FRCA website says that to pass you need to score about 53%. In the last week or so, I’ve been scoring 48-58% so, as things stand, my chances of passing are about 50-50. I’ve had lots of advice from the other SHOs and SpRs who have been through it and medical staffing have been very understanding. Now it’s all down to me and I’m determined to pass if only because I’ve invested far too much of my time and mental energy on this exam. Failure is not an option.

Right, now I’m off to learn which of the neuromuscular blocking drugs have active metabolites.

Wish me luck.